
IVF can fail for many different reasons, and a failed cycle does not necessarily mean that future treatment will fail. IVF involves several biological stages, from ovarian response and egg retrieval to fertilization, embryo development, implantation and early pregnancy. A problem at any of these stages can prevent a cycle from resulting in pregnancy.
The most important question after an unsuccessful IVF cycle is not simply “Why did IVF fail?” but “At which stage did the treatment stop progressing, and what does that tell us about the next step?”
A careful review of the complete IVF cycle can help identify factors that may be modifiable and distinguish them from factors that are difficult or impossible to predict. The American Society for Reproductive Medicine (ASRM) recommends a comprehensive review of the patient’s reproductive history, imaging and IVF cycle details when recurrent implantation failure is suspected.
Why Can IVF Fail?
IVF may fail because of problems with egg or embryo development, fertilization, sperm factors, uterine or endometrial factors, implantation, or because of biological factors that cannot be identified with current testing.
Common reasons include:
- Embryos with chromosomal abnormalities
- Age-related changes in egg quality
- Reduced ovarian response or a low number of eggs retrieved
- Fertilization problems
- Sperm-related factors
- Embryos stopping development before transfer
- Uterine abnormalities
- Endometrial or hormonal factors
- Failed implantation
- Pregnancy loss after implantation
- Medical conditions that affect fertility
- Factors that remain unexplained despite appropriate investigation
Importantly, IVF failure is rarely explained by one factor alone.
At Which Stage Did the IVF Cycle Fail?
Understanding the stage at which treatment stopped can make the previous cycle much more informative.
A typical IVF process includes:
- Ovarian stimulation
- Monitoring follicular development
- Egg retrieval
- Fertilization
- Embryo development
- Embryo selection and transfer
- Implantation
- Pregnancy development
For example, a cycle in which no mature eggs were retrieved is clinically different from a cycle in which several embryos developed but pregnancy did not occur after transfer.
The Human Fertilisation and Embryology Authority (HFEA) notes that an IVF cycle can stop progressing for several reasons, including inadequate response to stimulation, failure of fertilization or other factors before embryo transfer.
This is why reviewing the entire treatment sequence is more useful than describing every unsuccessful IVF attempt simply as “implantation failure.”
1. Chromosomal Abnormalities in the Embryo
One of the most important biological reasons an embryo may fail to implant or continue developing is a chromosomal abnormality.
An embryo can appear healthy under the microscope while still carrying an abnormal number of chromosomes. Embryo appearance, often called morphology, cannot by itself establish whether an embryo is chromosomally normal.
Age-related embryo aneuploidy is an important contributor to implantation failure. ASRM’s 2026 committee opinion identifies age-related aneuploidy as a principal cause of implantation failure because aneuploid blastocysts have very limited potential for sustained implantation and live birth.
This also helps explain why a patient can experience IVF failure despite having an embryo described as “good quality.”
Does a Good-Quality Embryo Guarantee Implantation?
No.
“Good-quality embryo” usually refers to its appearance and developmental characteristics under laboratory assessment. It does not guarantee chromosomal normality or successful implantation.
Even embryos that appear favorable may fail to implant because implantation depends on multiple biological factors involving both the embryo and the uterus.
2. Age and Egg Quality
Age is an important factor in IVF because the likelihood of chromosomal abnormalities in eggs and embryos increases with age.
Ovarian reserve and egg quantity are also relevant, but they are not the same as egg quality.
A patient may have a reasonable number of follicles or an adequate AMH level and still produce embryos that do not develop normally. Conversely, a patient with a lower ovarian reserve may still produce a transferable embryo.
For this reason, fertility prognosis should not be based on AMH or ovarian reserve alone.
HFEA also identifies age and the underlying cause of infertility among the factors that affect IVF success.
3. Too Few Eggs or Poor Ovarian Response
Some IVF cycles do not progress because the ovaries produce fewer follicles or mature eggs than expected.
Possible situations include:
- Low ovarian response to stimulation
- A small number of follicles developing
- Fewer eggs retrieved than expected
- A high proportion of immature eggs
- Difficulty obtaining suitable eggs
Ovarian reserve testing and ultrasound assessment can help a fertility specialist plan stimulation, but these tests cannot predict every aspect of how an individual cycle will perform.
Before starting another IVF cycle, the ovarian response from the previous treatment should be reviewed rather than automatically repeating the same protocol.
Dr. Emad Darwish provides ovarian stimulation and treatment of low ovarian reserve as part of his fertility and IVF services. Fertility & IVF Services

4. Fertilization May Not Occur
Having retrieved eggs does not necessarily mean that fertilization will occur normally.
Fertilization may be affected by:
- Egg maturity
- Sperm concentration
- Sperm motility
- Sperm morphology
- Previous fertilization history
- Other biological factors affecting the interaction between sperm and egg
When significant male-factor infertility or previous fertilization problems are present, ICSI may be considered in selected IVF cases.
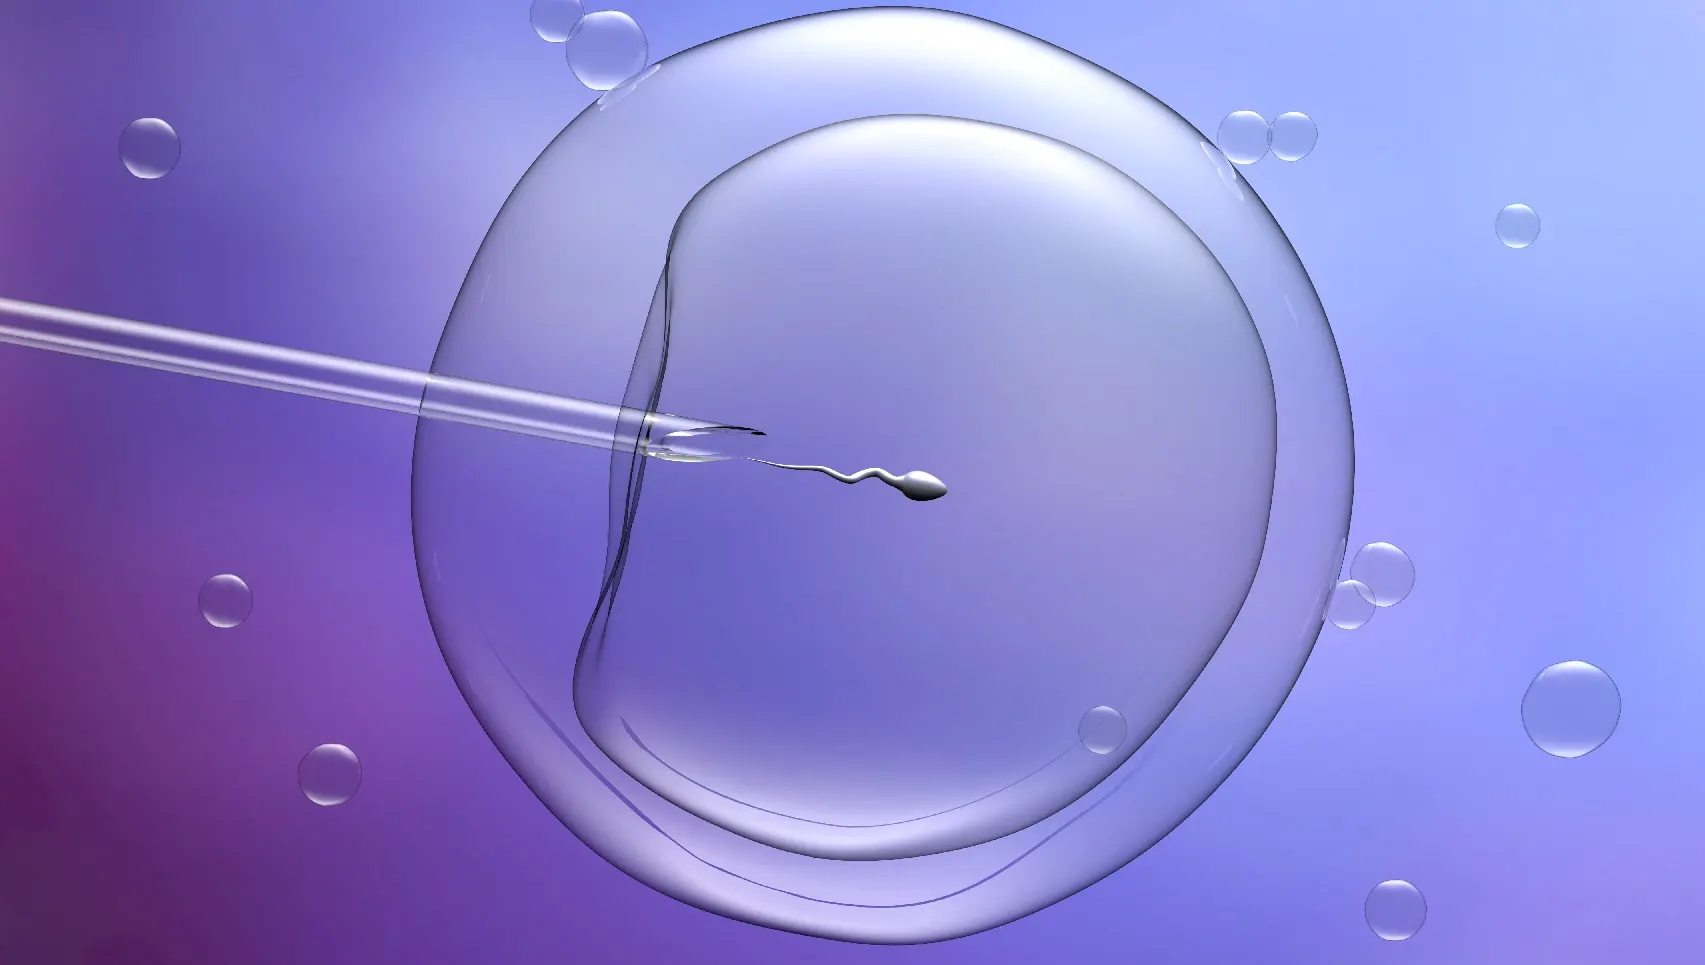
ICSI involves injecting a single sperm directly into a mature egg in the laboratory. Dr. Emad Darwish’s fertility services include ICSI for selected cases involving factors such as reduced sperm count, reduced motility or previous fertilization failure. ICSI and IVF Services
However, ICSI is not automatically required for every IVF patient. The decision should be based on the clinical circumstances and previous treatment results.
5. The Embryos May Stop Developing
Even after successful fertilization, not every embryo continues developing normally.
An IVF laboratory may observe embryos at different stages of development. Some may stop developing before reaching the stage considered suitable for transfer or freezing.
This can happen because of biological factors affecting the egg, sperm or embryo.
The number of eggs retrieved therefore does not tell the whole story.
The clinically relevant sequence is:
Eggs retrieved → mature eggs → fertilized eggs → developing embryos → transferable embryos
A substantial reduction at any point in this sequence can change the expected outcome of an IVF cycle.
6. Uterine or Endometrial Problems
An embryo needs an appropriate uterine environment for implantation.
Structural abnormalities inside the uterus may interfere with implantation. These can include:
- Endometrial polyps
- Intrauterine adhesions
- Certain fibroids
- Uterine structural abnormalities
- Hydrosalpinx in appropriate clinical circumstances
When recurrent implantation failure is suspected, ASRM recommends considering assessment of the endometrial cavity and relevant structural factors based on the patient’s history and previous IVF results.
Assessment may involve ultrasound, sonohysterography, hysteroscopy or other investigations when clinically indicated.
The goal is not to order every possible test after one unsuccessful transfer. Testing should be guided by the patient’s history and the pattern of previous treatment.
7. Hormonal and Endometrial Factors
The endometrium must undergo appropriate changes to support implantation.
Hormonal preparation, particularly progesterone exposure, is an important part of preparing the endometrium for embryo transfer.
However, an unsuccessful transfer does not automatically mean that the uterine lining was “not receptive.”
Many commercial tests and proposed treatments for implantation failure have been investigated, but the evidence is not strong enough to recommend routine use of every available test.
For example, ASRM’s 2026 guidance states that there is insufficient evidence to support routine use of endometrial receptivity testing such as ERA in recurrent implantation failure.
This is important because patients who experience IVF failure may encounter many tests marketed as ways to identify the reason an embryo did not implant. A medically appropriate investigation should distinguish evidence-supported assessment from tests that remain uncertain.
8. Implantation May Not Occur
Implantation occurs when an embryo attaches to and begins to penetrate the endometrium.
Successful implantation requires interaction between a viable embryo and a suitable uterine environment.
Failure of implantation can therefore occur even when:
- Fertilization was successful
- An embryo developed to the blastocyst stage
- The embryo looked good in the laboratory
- The embryo transfer itself was completed without an obvious complication
ASRM describes implantation failure as a complex area with inconsistent definitions and limited high-quality evidence for many proposed investigations and treatments.
A single failed embryo transfer does not automatically mean that a patient has a condition called recurrent implantation failure.
9. Sperm Factors Can Contribute to IVF Failure
Male fertility factors can affect IVF at several stages, including fertilization and embryo development.
A semen analysis generally assesses characteristics such as:
- Sperm concentration
- Motility
- Morphology
However, not every aspect of sperm function can be predicted from a routine semen analysis.
It is also important not to assume that sperm DNA fragmentation is automatically the explanation for recurrent IVF failure. Current ASRM guidance states that evidence is insufficient to recommend sperm DNA fragmentation testing routinely in patients with recurrent implantation failure.
Testing should therefore be based on the clinical situation rather than automatically added after every unsuccessful IVF cycle.
10. Some Causes of IVF Failure Remain Unexplained
This is one of the most important things patients should know.
Medicine cannot currently identify a specific cause for every unsuccessful IVF cycle.
A patient may undergo appropriate evaluation and still have no single explanation for why an embryo did not implant or why embryo development stopped.
That does not mean that treatment was necessarily performed incorrectly.
It also does not mean that another IVF attempt cannot succeed.
ASRM specifically notes that when no clear, correctable cause is identified after a detailed evaluation, extensive additional testing is not necessarily appropriate. Further embryo transfers may remain reasonable because many patients ultimately achieve pregnancy.
Can IVF Fail Even With a Euploid Embryo?
Yes.
A euploid embryo has the expected chromosome number based on the genetic test performed, but euploid status does not guarantee implantation or live birth.
Implantation also depends on factors involving the embryo, uterus and timing of the transfer.
ASRM notes that even in recurrent implantation failure, evidence is insufficient to conclude that PGT-A universally improves live-birth rates. Its use should therefore be considered in the context of the individual patient rather than presented as a guaranteed solution to IVF failure.
What Should I Do After a Failed IVF Cycle?
The next step should usually be a structured review of the previous IVF cycle, rather than immediately starting another cycle without understanding what happened.
Your fertility specialist may review:
Ovarian response
- How many follicles developed?
- How many eggs were retrieved?
- How many were mature?
Fertilization
- How many eggs fertilized?
- Was conventional IVF or ICSI used?
- Was there previous fertilization failure?
Embryo development
- How many embryos developed?
- Did embryos reach the blastocyst stage?
- Were embryos frozen?
- Was genetic testing performed?
Embryo transfer
- Was an embryo transferred?
- Was the transfer fresh or frozen?
- Were there any technical or uterine factors that required consideration?
Pregnancy outcome
- Was there no implantation?
- Was there a biochemical pregnancy?
- Was there a clinical pregnancy followed by miscarriage?
These are different clinical situations and should not automatically be treated in the same way.
Does One Failed IVF Cycle Mean I Will Need Another?
Not necessarily.
A patient may have frozen embryos remaining from the original IVF cycle, meaning that a frozen embryo transfer may be possible without repeating ovarian stimulation and egg retrieval.
If no suitable embryos remain, another IVF cycle may be considered depending on the patient’s prognosis and treatment goals.
The decision should be individualized according to age, ovarian reserve, fertility diagnosis, previous IVF response, embryo development and the outcome of previous transfers.
Dr. Emad Darwish offers embryo freezing as part of his fertility services, allowing suitable embryos created during IVF to be preserved for future treatment. Embryo Freezing
When Is It Considered Recurrent IVF Failure?
“Recurrent IVF failure” and “recurrent implantation failure” are not interchangeable terms, and there is no single universally accepted definition of recurrent implantation failure.
The current ASRM definition uses the estimated number of good-quality blastocysts required to reach a 95% cumulative chance of a positive pregnancy test, taking factors such as embryo ploidy and patient characteristics into account.
This means that the number of failed transfers alone does not tell the complete story.
When recurrent implantation failure is suspected, the evaluation should be individualized and may include review of:
- Previous IVF cycles
- Embryo characteristics
- Uterine anatomy
- Endometrial factors
- Relevant hormonal factors
- Genetic considerations
- The patient’s age and reproductive history
Dr. Emad Darwish provides recurrent IVF failure treatment involving reassessment of the factors relevant to previous unsuccessful treatment and development of an individualized strategy. Recurrent IVF Failure Treatment
Which Tests Are Not Automatically Needed After IVF Failure?
IVF failure can make patients understandably want to investigate everything at once.
However, more testing does not necessarily mean better treatment.
ASRM’s 2026 guidance does not recommend routine use of several proposed investigations or treatments for recurrent implantation failure, including endometrial receptivity panels, endometrial scratching, certain immune therapies and sperm DNA fragmentation testing for this specific indication.
This does not mean these subjects are never relevant in medicine. It means that they should not automatically be presented as standard investigations for every patient after IVF failure.
A fertility specialist should determine which investigations are justified by the individual clinical history.
Can IVF Work After a Failed Cycle?
Yes. A failed IVF cycle does not by itself mean that future IVF treatment will fail.
The likelihood of success with another attempt depends on the reason for the previous outcome and the patient’s overall prognosis.
Sometimes the next step is another embryo transfer. Sometimes a new IVF cycle is appropriate. In other situations, additional assessment or a change in treatment strategy may be more appropriate.
The important point is to avoid treating every failed cycle in exactly the same way.
What Questions Should I Ask After Failed IVF?
Before starting another treatment cycle, consider asking:
- At which stage did my previous IVF cycle stop progressing?
- How did my ovaries respond to stimulation?
- How many eggs were mature?
- Was fertilization lower than expected?
- How did the embryos develop?
- Do I have suitable frozen embryos?
- Was there a reason to reassess the uterus or endometrium?
- Does my age or ovarian reserve change the expected benefit of another cycle?
- Should the treatment protocol be changed?
- Which additional tests are actually supported by evidence in my situation?
These questions can make a follow-up consultation much more useful.
When Should I See a Fertility Specialist After Failed IVF?
A fertility consultation is particularly useful when you want to understand why the previous treatment did not work and whether another attempt is medically reasonable.
Before another IVF cycle, a comprehensive fertility assessment can review both partners and may include hormonal testing, semen analysis, ultrasound assessment and evaluation of the uterus and ovaries. Additional investigations can be considered when clinically indicated. Pre-IVF Assessment and Fertility Testing
Dr. Emad Darwish is a Consultant in Obstetrics and Gynecology and Consultant in Reproductive Medicine and IVF, with more than 16 years of clinical and academic experience in infertility treatment and assisted reproductive medicine. His practice describes an individualized approach based on each patient’s condition and previous treatment history. About Dr. Emad Darwish
If you have experienced an unsuccessful IVF cycle, the next step does not have to be another IVF cycle immediately. A detailed review can help determine what happened, what can reasonably be investigated, and whether another treatment approach may be appropriate.
Book an IVF consultation with Dr. Emad Darwish to discuss your previous treatment and possible next steps.
Medical disclaimer: This content is intended for general educational purposes and does not replace individualized medical assessment. Fertility treatment recommendations depend on medical history, test results, age, reproductive goals and other individual factors.
FAQ
Why does IVF fail?
IVF can fail because of problems with embryo development, chromosomal abnormalities, egg or sperm factors, fertilization, uterine or endometrial factors, implantation, or pregnancy development. Sometimes no single cause can be identified.
Can IVF fail because of embryo quality?
Yes. Embryo development and chromosomal status can affect implantation and pregnancy. An embryo that looks good under the microscope is not necessarily chromosomally normal.
Why does IVF fail with a good-quality embryo?
A good-quality embryo does not guarantee implantation. Chromosomal factors that cannot be identified by morphology alone, uterine factors and other biological factors can contribute to implantation failure.
Can IVF fail because of the uterus?
Yes. Uterine structural abnormalities and certain endometrial or tubal factors can affect implantation. When recurrent implantation failure is suspected, targeted assessment of the uterine cavity may be appropriate.
Does one failed IVF cycle mean the next will fail?
No. A failed cycle does not automatically predict failure of future treatment. The previous cycle should be reviewed to understand what happened and whether anything should be changed.
Should I have more tests after failed IVF?
Not necessarily. Additional testing should be based on the patient’s history and previous IVF results. ASRM does not recommend routine use of several proposed tests and treatments for recurrent implantation failure because evidence remains insufficient.
What is recurrent implantation failure?
There is no universally accepted definition. ASRM’s current approach defines recurrent implantation failure according to failure to achieve a positive pregnancy test after transferring an estimated number of good-quality blastocysts sufficient to reach a 95% cumulative probability, taking embryo ploidy and patient characteristics into account.
Can IVF work after repeated failure?
Yes, it can. The appropriate next step depends on why previous treatment was unsuccessful, the patient’s prognosis and whether a correctable factor has been identified.








Contact Us.
Contact the clinic to ask about appointment availability or arrange a consultation with Dr. Emad Darwish.
