
The main difference between IVF and ICSI is how fertilization happens in the laboratory.
In conventional IVF, retrieved eggs are placed with prepared sperm and fertilization is allowed to occur without directly injecting sperm into the egg. In ICSI, or intracytoplasmic sperm injection, an embryologist selects a single sperm and injects it directly into a mature egg.
ICSI is therefore not a completely separate fertility treatment from IVF. It is a specialized fertilization technique that can be used within an IVF cycle. Ovarian stimulation, monitoring, egg retrieval, embryo culture and embryo transfer are generally similar. The key difference occurs at the fertilization stage.
IVF vs ICSI at a Glance
|
Factor |
Conventional IVF |
ICSI |
|
Fertilization method |
Eggs are placed with prepared sperm in the laboratory |
One sperm is injected directly into a mature egg |
|
Direct sperm injection |
No |
Yes |
|
Common reason for use |
IVF is appropriate for a wide range of fertility problems when conventional fertilization is suitable |
Often used when sperm-related factors may make conventional fertilization difficult |
|
Previous fertilization failure |
May influence the decision to change technique |
May be considered after failed or very poor fertilization with conventional IVF |
|
Surgically retrieved sperm |
Conventional IVF may not be suitable |
ICSI is generally used |
|
Patient treatment steps |
Ovarian stimulation, monitoring, egg retrieval and embryo transfer |
Usually the same |
|
Automatically more successful? |
No treatment is universally better |
Routine ICSI has not been shown to improve live-birth outcomes when there is no appropriate indication |
Current guidance emphasizes that ICSI should be selected because there is a clinical reason for direct sperm injection, rather than simply because it is a more technically assisted method.
What Is IVF?
In vitro fertilization (IVF) is an assisted reproductive treatment in which eggs are collected from the ovaries and fertilized with sperm in a laboratory.
A typical IVF cycle may involve:
- Ovarian stimulation
- Ultrasound and, when appropriate, hormonal monitoring
- Egg retrieval
- Preparation of the sperm sample
- Fertilization in the laboratory
- Embryo culture
- Embryo transfer or embryo freezing when appropriate
- Pregnancy testing at the recommended time
With conventional IVF fertilization, prepared sperm are placed with the retrieved eggs and a sperm must enter an egg without being directly injected into it.
IVF may be considered for different fertility problems, including tubal-factor infertility, some ovulation problems, unexplained infertility and other situations where assisted reproduction is clinically appropriate. The exact treatment depends on the results of the fertility assessment rather than on the diagnosis alone.
Patients considering assisted reproduction can review Dr. Emad Darwish’s available fertility and IVF services, which include IVF, ICSI and pre-IVF fertility assessment.
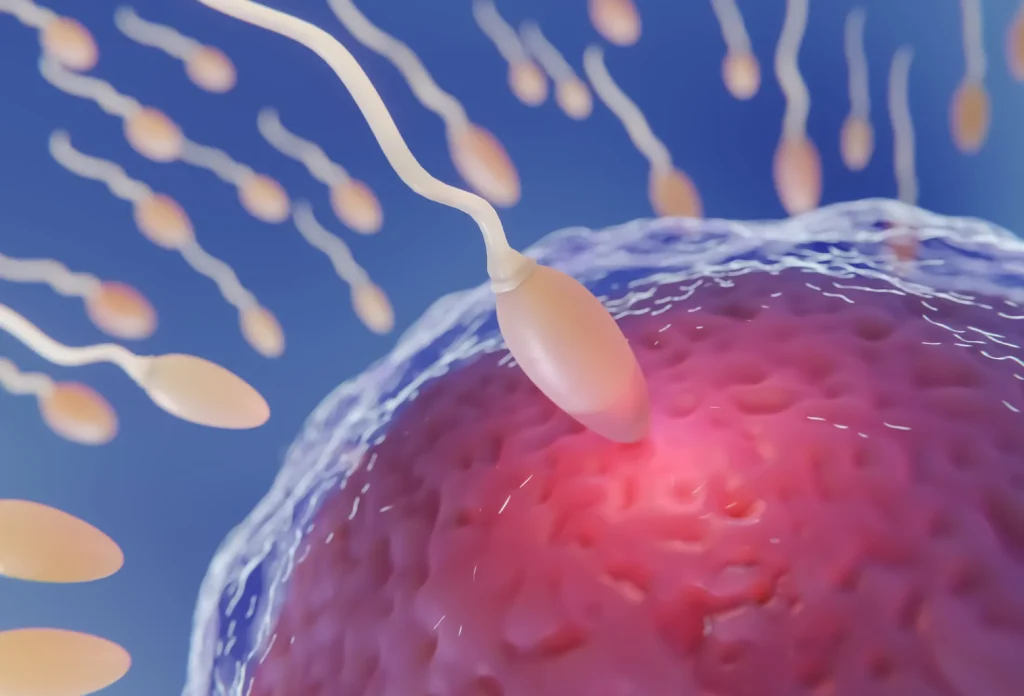
What Is ICSI?
Intracytoplasmic sperm injection, or ICSI, is a laboratory fertilization technique performed as part of IVF.
Instead of placing sperm around the egg and waiting for fertilization to occur, an embryologist injects one selected sperm directly into a mature egg.
This bypasses some of the steps the sperm would otherwise need to complete before entering the egg. It can therefore be useful when sperm-related factors make conventional fertilization less likely.
After fertilization, embryos created through ICSI are cultured and managed in broadly the same way as embryos created through conventional IVF.
Where Exactly Do IVF and ICSI Differ?
The difference occurs after the eggs have been retrieved and the sperm sample has been prepared.
Conventional IVF
Prepared sperm are placed together with the eggs in a culture environment. A sperm must interact with and enter the egg without direct injection.
ICSI
The embryologist identifies a mature egg and injects one sperm directly into it using specialized laboratory equipment.
After this stage, successfully fertilized eggs can continue developing into embryos for possible transfer or freezing.
This means patients usually do not undergo a separate stimulation or egg retrieval simply because ICSI is being used. ICSI changes the fertilization technique inside the laboratory, not the basic structure of the IVF cycle.
When May ICSI Be Recommended?
ICSI is particularly relevant when there is evidence that sperm may have difficulty fertilizing an egg through conventional IVF.
Examples include:
- Significantly abnormal semen parameters, such as reduced sperm concentration or motility
- Certain cases involving abnormal sperm morphology
- Sperm obtained through surgical sperm retrieval
- Previous IVF in which none or very few eggs fertilized
- Use of frozen-thawed eggs
- Selected genetic-testing situations in which the laboratory has a specific reason to use ICSI
NICE’s 2026 fertility guidance recommends ICSI for surgically retrieved sperm and frozen-thawed oocytes and advises considering it when semen parameters are abnormal or when a previous IVF cycle resulted in failed or very poor fertilization.
HFEA guidance similarly identifies very low sperm count, reduced sperm movement, abnormal morphology, previous poor fertilization and surgically retrieved sperm as common reasons ICSI may be recommended.
Is ICSI Better Than Conventional IVF?
ICSI is not automatically better than conventional IVF.
It can be highly useful when there is a specific fertilization problem to overcome, particularly in male-factor infertility. However, using more laboratory intervention does not necessarily translate into a higher chance of live birth for every patient.
The American Society for Reproductive Medicine states in its 2026 committee opinion that routine ICSI in patients without male-factor infertility or previous fertilization failure does not improve live-birth rates compared with conventional IVF. ASRM also reports no established live-birth advantage from routine ICSI solely because of advanced maternal age, diminished ovarian reserve or low egg yield.
HFEA likewise notes that ICSI success rates tend to be similar to IVF overall and does not publish separate ICSI success statistics for this reason.
The better question is therefore not:
“Which technique is more advanced?”
It is:
“Is there a clinical reason that direct sperm injection is likely to help in this IVF cycle?”
Does ICSI Increase Fertilization?
ICSI may help achieve fertilization when sperm-related factors make it difficult for sperm to enter the egg or when previous conventional IVF resulted in unexpectedly poor or failed fertilization.
However, fertilization is not the same as pregnancy or live birth.
An egg can fertilize but fail to develop into a transferable embryo. An embryo can be transferred without implanting. Pregnancy outcomes are influenced by multiple factors beyond the method used to fertilize the egg.
ASRM therefore emphasizes live birth as the clinically important outcome and advises against assuming that improvement in an intermediate laboratory outcome automatically means better overall reproductive results.
Does ICSI Guarantee Fertilization?
No.
Injecting sperm directly into an egg does not guarantee that the egg will fertilize normally, continue dividing, become a suitable embryo, implant or result in a live birth.
ICSI can address a specific barrier to sperm entering the egg, but it cannot overcome every possible issue involving egg quality, embryo development or other factors affecting fertility treatment.
HFEA specifically notes that ICSI may be unlikely to help when previous fertilization problems were related mainly to poor-quality or immature eggs rather than sperm-related factors.
How Do Doctors Choose Between IVF and ICSI?
The decision should follow an individualized fertility evaluation.
Important factors may include:
- Semen analysis results
- Previous IVF and fertilization history
- How sperm will be obtained
- Whether frozen eggs are being used
- The number and maturity of retrieved eggs
- The underlying fertility diagnosis
- Planned laboratory or genetic procedures
- Previous treatment history
Before IVF treatment, assessment may include semen analysis, hormonal investigations, ultrasound and evaluation of the uterus and ovaries depending on the clinical situation. Dr. Emad Darwish’s fertility assessment and IVF services include pre-IVF assessment alongside IVF and ICSI treatment.
This assessment is important because two patients undergoing IVF may have very different reasons for choosing conventional fertilization or ICSI.
What Happens During an IVF Cycle With ICSI?
From the patient’s perspective, much of an IVF cycle with ICSI is similar to conventional IVF.
1. Fertility Assessment
The fertility specialist reviews the medical and reproductive history and relevant investigations for both partners.
2. Ovarian Stimulation and Monitoring
Medication may be used to stimulate the ovaries to develop multiple follicles. Response is monitored according to the treatment protocol.
3. Egg Retrieval
Eggs are collected from the ovaries using the planned retrieval procedure.
4. Fertilization
This is the stage where the treatments differ.
With conventional IVF, eggs and prepared sperm are placed together.
With ICSI, one sperm is injected directly into each suitable mature egg.
5. Embryo Culture
Successfully fertilized eggs are monitored as they develop into embryos.
6. Embryo Transfer or Freezing
Depending on the treatment plan and embryo development, an embryo may be transferred or suitable embryos may be frozen for later use.
The overall IVF process and exact timeline can vary according to the protocol and individual clinical circumstances.
What Factors Affect IVF or ICSI Outcomes?
The fertilization technique is only one part of assisted reproduction.
Treatment outcomes can also be influenced by factors such as:
- Age
- Ovarian reserve and ovarian response
- Underlying fertility diagnosis
- Sperm-related factors
- Egg and embryo development
- Previous fertility-treatment history
- The individualized treatment protocol
HFEA notes that IVF success depends substantially on age and the cause of infertility, while ICSI does not remove the other factors that influence whether treatment ultimately results in pregnancy or birth.
For this reason, comparing IVF and ICSI only by asking which has a higher “success rate” can be misleading.
Are There Additional Risks With ICSI?
ICSI involves additional laboratory manipulation of the egg.
HFEA notes that there is a risk that some eggs may be damaged during preparation or injection. It also reports that research has examined possible associations between ICSI and certain genetic or developmental problems, although separating the effect of the procedure from the underlying male infertility can be difficult.
When severe male-factor infertility may have an underlying genetic cause, additional investigation or genetic counselling may sometimes be appropriate before treatment.
Patients undergoing ICSI also remain exposed to the usual risks associated with the wider IVF treatment cycle.
Is ICSI More Expensive Than IVF?
ICSI may involve an additional laboratory charge because it requires specialized embryology procedures beyond conventional insemination.
The exact cost varies between clinics and according to what is included in the treatment package. Medication, testing, embryo freezing and other procedures may also be charged separately.
Current pricing should therefore be confirmed directly with the clinic rather than relying on a general online figure.
IVF or ICSI: Which One Might Be Appropriate for You?
The choice should be based on the reason for infertility and the results of your fertility assessment.
Conventional IVF may be appropriate when sperm parameters and treatment history do not indicate a need for direct sperm injection.
ICSI may be appropriate when significant sperm-related factors, surgically retrieved sperm, previous poor fertilization or another specific clinical indication is present.
ICSI should not be considered automatically superior simply because it uses more laboratory intervention. Current evidence supports using it selectively when there is a reason it may improve the chance of fertilization.
Dr. Emad Darwish is a Consultant in Reproductive Medicine and IVF, with fertility, IVF and ICSI included within his clinical services.
If you are preparing for fertility treatment or have previously experienced poor fertilization during IVF, an individualized assessment can help determine which fertilization method is more appropriate for your circumstances.
You can book an appointment with Dr. Emad Darwish or contact the clinic to discuss your fertility assessment and treatment options.
Medical disclaimer: This content is intended for general educational purposes and does not replace individualized medical assessment. Fertility treatment recommendations depend on medical history, test results, age, reproductive goals and other individual factors.
FAQ
Is ICSI the same as IVF?
No. ICSI is a fertilization technique used within an IVF cycle. The stimulation, egg retrieval, embryo culture and embryo-transfer stages are generally similar, but the fertilization method differs.
Can ICSI be performed without IVF?
ICSI requires eggs to be retrieved and fertilized in an embryology laboratory, so it is performed as part of an IVF treatment cycle. Clinics may refer to the treatment simply as “ICSI,” but clinically it is IVF using ICSI as the method of fertilization.
Is ICSI more successful than IVF?
Not for every patient. ICSI can be valuable when there is a specific sperm-related problem or previous fertilization failure, but routine ICSI has not been shown to improve live-birth rates in patients without an appropriate indication.
Who may need ICSI?
ICSI may be considered when semen parameters are significantly abnormal, sperm is surgically retrieved, previous IVF resulted in failed or very poor fertilization, or certain other laboratory circumstances make direct sperm injection appropriate.
Does ICSI guarantee that an egg will fertilize?
No. ICSI can help overcome some barriers to fertilization, but not every injected egg will fertilize normally or develop into an embryo. It also cannot guarantee implantation, pregnancy or live birth.
Is ICSI recommended for low AMH?
Low AMH or diminished ovarian reserve alone is not evidence that ICSI will improve live-birth outcomes. ASRM’s 2026 guidance reports no demonstrated benefit from routine ICSI solely for diminished ovarian reserve or low oocyte yield when there is no male-factor indication.
Is ICSI recommended because of female age?
Age is an important factor in fertility treatment outcomes, but advanced maternal age alone is not a reason to assume ICSI will produce better live-birth outcomes than conventional IVF. Treatment should be selected according to the complete clinical assessment.
Is ICSI painful?
ICSI itself is performed on the retrieved egg in the embryology laboratory, so the patient does not feel the sperm-injection procedure. The wider IVF cycle still involves stimulation, monitoring and egg retrieval, which may involve discomfort or side effects.
How will I know whether I need IVF or ICSI?
A fertility specialist usually considers semen analysis, previous treatment results, the method of sperm retrieval, egg-related factors and the wider fertility diagnosis before recommending the fertilization technique.



تواصل معنا
تواصل معنا اليوم للحصول على الاستشارة المتخصصة، وحجز موعد، والدعم المناسب لاحتياجاتك خلال رحلة علاج تأخر الإنجاب وتحقيق حلم الأبوة والأمومة
